Lifestyle

You can add some category description here.

On the Unintended Impact of Health Insurance

By Oladoja M.O

Encouraging is an understatement when you consider how far we’ve come in health insurance coverage in Nigeria. It’s pleasing to see health insurance gradually becoming a bigger part of Nigeria’s healthcare conversation. More people enrolling, more attention to coverage, and the ongoing expansion and adjustment of health insurance programmes all point in one direction: we are taking financial protection in healthcare more seriously.

For a country where illness can quickly become a financial crisis, this is certainly worth celebrating.

But while we celebrate the numbers, we should also ask: what happens when the insured person actually walks into a hospital?

There appears to be an emerging culture around insured patients that we should not allow to become normal. 

You hear it in the phrase, “they are under HMO.”

Some patients have experienced delayed attention, dismissive attitudes and poor communication simply because their care is being financed through insurance. There are stories of patients being made to feel like a burden because someone else, rather than the patient standing in front of the provider, is paying the bill.

A social media post that circulated recently brought this into the open. Someone associated with a healthcare facility made a derogatory remark about a family who had come to receive care under health insurance. 

The concern isn’t just the statement, but the thought of what those people and many others may have experienced before that statement ever appeared online, and the comments under the post so proved a lot that people had been put through.

That was the one that became public.

How many others never do? An this is where health insurance meets something much deeper in our society: classism.

We already know that the ability to pay can influence how people experience healthcare. Health insurance is meant reduce that inequality, not create another label through which patients are treated differently.

And to note, quality of care is not just about eventually receiving treatment. It includes how the patient is received, how long they wait, how they are spoken to and whether they retain their dignity while receiving care.

Hearing from both sides, healthcare providers do have legitimate concerns about the economics of health insurance. Tariffs vs actual treatment cost, uncertainty of reimbursement, etc., factually, running a healthcare facility is expensive, and particularly for private providers, sustainability cannot be ignored. 

But while these are legitimate concern, it is a big problem when the gap is pushed down to the patient.

There are concerns about patients being asked to make additional payments even when the service is covered by their insurance, attempts to recover inadequate reimbursement through duplicating charges or claiming for services a patient did not actually receive, and patients routinely being asked to pay part of the cost even when the treatment falls within their insurance coverage.

Yes, this is not to indict healthcare providers, but we can all agree that these concerns are too important to ignore.

When the provider and insurer disagree about the cost of care, the patient should not quietly become the person who settles the disagreement.

I remember asking a question during a session at the maiden African Primary Health Care Forum in 2025, that how do we balance healthcare provision with the intention to make profit, without allowing profit to override the people who should remain at the centre?

Unfortunately, there was no easy answer. Truthfully, it is tricky.

Providers need to survive, insurers need to remain financially sustainable and government cannot carry every cost in the health system. Yet somewhere between these competing interests is the person who became sick in the first place.

This is why the response cannot simply be “let’s increase the tariffs” or “let providers absorb the loss.” Neither is sustainable. If tariffs rise without considering the wider financing burden, patients may eventually bear the cost. If providers continually operate below sustainable levels, quality of care will suffer.

And that’s why there’s need for a dive at whole financing structure.

The government needs to examine the real costs and obligations of healthcare provision and identify where targeted fiscal relief or support can ease pressure on providers without simply shifting it to patients. Insurers must reimburse realistically. Providers must be allowed to remain viable, but must also remain accountable for what they provide and claim.

Monitoring must become active!

Where systems have gaps, people will eventually find ways to exploit them. Claims should be monitored. Unusual billing patterns should raise questions. Services billed should correspond with services delivered. Patient complaints should not disappear into administrative files, and repeated non-compliance should have consequences.

This is not about setting providers against insurers. Everyone has a part to play.

The government must regulate and create an environment where healthcare financing is sustainable. Insurers must protect the integrity of the pool and pay fairly. Providers must deliver quality care without making patients pay for every weakness in the system. Patients must also understand their rights and speak up when something is wrong.

The point is not to remove profit from healthcare. That is neither realistic nor desirable. The point is to ensure that profit does not become more important than the person healthcare is supposed to serve.

That is the balance we need.

Because ultimately, the success of health insurance should not be measured only by how many people have been enrolled. 

It should also ask what those people experience when they finally need care, if the insurance actually protects them, if they can walk into a facility without being treated as a lesser patient because they are “under HMO”, if they receive the care they are entitled to without becoming the financial solution to a disagreement between provider and insurer?

Expansion of health insurance in Nigeria must weigh in on these questions. 

We are still building this system, and that gives us an opportunity to correct what is beginning to go wrong before it becomes normal.

Health insurance is too important to lose the very person it was created to protect.

The patient must remain at the centre, not at the receiving end of the system.

And the unintended negative stretches of this beautiful system must be confronted and, while we still can, nip in the bud.

Oladoja M.O. (Oladoja Mark Olamilekan) writes from Abuja and can be reached at: mayokunmark@gmail.com.

FG Directs Hospitals to Strengthen Ebola Preparedness, Equip Isolation Centres

By Sabiu Abdullahi

The Federal Government has directed hospitals and other health facilities across Nigeria to strengthen their isolation units and ensure the availability of protective equipment and essential medical supplies as part of efforts to prevent and manage any possible outbreak of Ebola Virus Disease (EVD).

The directive was disclosed by Dr Yunus Mohammed Eze, Deputy Head of Clinical Services at the Federal Medical Centre (FMC), Birnin Kudu, Jigawa State, during an interview with journalists.

Eze said the Federal Ministry of Health had instructed health facilities nationwide to put emergency response arrangements in place to ensure the prompt identification, isolation and management of suspected Ebola cases.

He explained that FMC Birnin Kudu had responded by strengthening its isolation unit and placing healthcare workers on alert.

“The Federal Government, through the Ministry of Health, communicated with health facilities across the country and directed them to prepare their isolation units and ensure that everything required to protect healthcare workers and manage affected patients was available,” he said.

According to him, the hospital management immediately implemented the directive and made arrangements to isolate suspected cases and refer patients to designated treatment centres where necessary.

Hospital intensifies public awareness

Eze said the hospital had also stepped up public health education through its Infectious Diseases Unit and Community Medicine Unit to raise awareness about infectious diseases and preventive practices.

He added that the facility was working with the Jigawa State Media Corporation to educate residents on disease prevention and the importance of promptly reporting suspected cases.

The medical expert further disclosed that healthcare workers regularly educate patients and visitors at the hospital, encouraging them to pass the information on to their families and communities.

The preparedness measures are intended to strengthen Nigeria’s capacity to detect and respond quickly to any suspected Ebola case, while ensuring the safety of healthcare workers and patients.

The Daily Reality

NCDC Approves ₦100,000 Weekly Support for People Isolated Over Ebola Outbreak

By Sabiu Abdullahi

The Nigeria Centre for Disease Control and Prevention (NCDC) has approved an emergency payment of ₦100,000 per week for individuals placed in isolation or quarantine as part of efforts to contain the Ebola outbreak in the Federal Capital Territory (FCT).

The agency’s Director-General, Dr Jide Idris, disclosed this during a press briefing in Abuja on Sunday, October 25, 2026.

According to Idris, the financial support was introduced after some individuals being monitored raised concerns about the cost of feeding, accommodation and providing for their families while in isolation.

“We introduced the payment after some contacts raised concerns about feeding, accommodation and how to take care of their families while under monitoring. The support is to ease their financial burden and encourage them to cooperate with health officials,” Idris said.

He explained that the payment was not part of the initial outbreak response plan but became necessary after the concerns were raised.

“This was not planned for, but it is an emergency. We will continue to review it as we go along,” he said.

The NCDC director-general also urged state governments to make adequate financial and logistical preparations for public health emergencies.

Idris stressed that the responsibility for containing disease outbreaks should not be left to the FCT alone, noting the importance of preparedness and cooperation among state governments.

The emergency support is intended to ease the financial pressure on affected individuals while they comply with isolation and quarantine measures.

The Strong Thing that the 2023 Election Did to Banky W

By Ugochukwu Ugwuanyi

Full disclosure: I had the song “Strong Ting” by Banky W on auto-repeat in my music playlist while in the world. Be that as it may, that’s by the way!

“…But David encouraged himself in the Lord his God.”

Nigerian singer and filmmaker Bankole Wellington, better known as Banky W, relived this aspect of 1 Samuel 30:6 after losing his bid for the Eti-Osa Federal Constituency seat in the House of Representatives during the 2023 general election. Finding courage in the Lord like David did when distraught and threatened, Banky found clarity amidst the maze and melancholy.

We will get to this momentarily, but not before ridding the elephant in the room. That would be the streets and cynics taunting: “Who send am go run for election?” or something like, “Couldn’t he have seen that the odds were stacked against him?” If his instincts couldn’t, how about his spiritual discernment as a man of God? The comment section also has others asking why he’s giving up so easily by not trying “his luck again” or worming his way into the good graces of the prevailing political establishment.

Politicians, particularly of the Nigerian stock, are Pollyannaish in nature. In fact, it seems a major qualification to be a politician in Nigeria is an overbloated sense of one’s worth or extreme optimism. They hardly give up on their ambitions. Banky W not being on the ballot in this round of elections affirms his epiphany or Road to Damascus experience.

In a post on his Instagram page this Thursday, @bankywellington wrote, “In 2023 I lost an election. And while the experience inspired me in many ways, it also broke my heart into a million little pieces. When the dust settled, I took those pieces back to God. And I surrendered.” We commend him for turning to God like David did when he seemingly lost it all. How great is the Lord to have successfully mended a heart shattered into a million fragments! This is why, upon life’s billows, people should run to, not away from Him. Perhaps those jostling for political positions in Nigeria’s 2027 election will, by Banky’s testimony, learn how to snatch victory from the jaws of defeat when the chips are down.

It is in the character of many to pick a quarrel with God when things don’t work out as planned. Such persons should heed the admonition of the tried and triumphant Job by acquainting themselves with God, and be at peace: so that good can come unto them (Job 22:21). If only the aggrieved had a sense of the big picture, they would see that the good Lord has not called the seed of Jacob to seek Him in vain. Even when you have acted in spite, or volitionally, the loving Father’s penchant for turning a mess into a message makes Him to bestow on you “a crown of beauty instead of ashes, the oil of joy instead of mourning, and a garment of praise instead of a spirit of despair” (Isaiah 61:3).

Banky W is definitely better off currently than he would have been holding a political office. That’s probably why he is out of the 2027 polls. This isn’t about him working as a teacher and leader at Union College in the United States, but about what his koinonia with the Holy Spirit can bring. We congratulate the music label boss, who significantly propelled the career of Grammy-grabbing Wizkid as the EME honcho, for being able to expressly hear from the Lord and align with the Almighty’s will for his life. Hear him again: “One year later, I’m reminded that sometimes what feels like the end of your story is really just God turning the page. The election didn’t go the way I hoped. But God’s plans for my life are bigger than the plans I had for myself.”

We can now see that all things work for the good of those who love him, who have been called according to his purpose. If not for his loss at the polls, Banky wouldn’t have come to a better and beneficial understanding of God. This brings us back to whether he didn’t get Heaven’s green light before initially throwing his hat in the ring. That could also have been God’s means of helping the prodigiously talented celebrity actualise destiny. Notice that while acknowledging God’s expansion of his assignments, he didn’t list politics. As it were, not even the “P” in his P.Banks moniker was cited as representing “politician.” “I used to joke that the ‘P’ in P.Banks stood for Professor, not Pastor. I guess God heard and said, ‘Why not both?’” he wrote. It pays greatly to know and follow the divine will for one’s life.

The consciousness of God in your corner would never allow you to turn the curveball life throws at you into an own goal. But this requires subjecting your will to His on every matter. That word “surrendered,” as used by the former secular singer, is basically what is needed. So many people have missed it in life and destiny because they couldn’t yield. We advisedly used “couldn’t” since some people are eager to be led but don’t know how. Come to think of it, how can someone not desire being led by the Lord? The fact that politicians are no longer making a singsong of “follow who know road” in this electioneering season doesn’t mean that the street wisdom is no longer valid. How much more the privilege of having to follow the Road (no pun intended – John 14:6).

King David absolutely knew what he was talking about when he declared in Psalm 23, “The LORD is my shepherd; I shall not want.” The ensuing verses list other amazing benefits. God rewards those who diligently seek Him. Graciously, He is not hard to find. Verses in the Old and New Testaments affirm this much. Jeremiah 29:13: “You will seek me and find me when you seek me with all your heart.” Matthew 7:7: “Ask and it will be given to you; seek, and you will find; knock and the door will be opened to you.” In reality, He is the one actually doing the seeking. This is why He said in Revelation 3:20, “Behold, I stand at the door, and knock: if any man hear my voice, and open the door, I will come in to him, and will sup with him, and he with me.”

Nonetheless, without bothering ourselves with the semantic symmetry between seeking and following God, the Good News is that both spiritual endeavours are enabled by the same manual – the Bible. You seek and know God by studying and meditating on His Word. For sure, there are Sons who can hear God directly and clearly; they all started from somewhere – a hunger for the Word of God. You’ve got to begin from the known to the unknown. In the main, be sure not to dissent as you discern!

VIS Ugochukwu is a sage, storyteller, and branding specialist who welcomes feedback at nmiringwu@gmail.com.

Poverty, School Dropout Increase HIV Risks Among Girls, AHF Warns

By Sabiu Abdullahi

The AIDS Healthcare Foundation (AHF) has urged federal and state governments to adopt and fund the Girls Act model to reduce HIV infections among adolescent girls and young women, citing poverty, school dropout and limited access to information as factors that increase their vulnerability.

The advocacy group made the call on Tuesday during activities to mark the International Day of the Girl Child in Abuja.

AHF said although progress had been made in the global fight against HIV/AIDS, adolescent girls and young women continued to face a disproportionate risk of infection, particularly in sub-Saharan Africa.

Steve Aborisade, AHF’s Advocacy Lead, cited data from the Joint United Nations Programme on HIV/AIDS (UNAIDS), which indicate that women account for more than half of people living with HIV globally and about 60 per cent in sub-Saharan Africa.

The data also show that adolescent girls and young women aged 15 to 24 are up to two to three times more likely to acquire HIV than males in the same age group.

“Adolescent girls and young women aged 15 to 24 years are up to two to three times more likely to acquire HIV than young males of the same age.

“Biologically, women face a roughly two-fold higher acquisition risk per unprotected heterosexual act due to a larger mucosal surface area and longer exposure to seminal fluids.”

The report further highlighted challenges that prevent adolescents from accessing HIV testing, including physiological, psychological, legal and social barriers.

“Adolescents aged 10 to 19 years face distinct physiological, psychological, legal and social factors that make them disproportionately vulnerable to low uptake of HIV testing,” the data indicated.

AHF said gender inequality, poverty and inadequate information often restrict girls’ ability to make decisions about their health and personal lives.

“A girl who cannot afford menstrual products, who has dropped out of school, or who depends on others for money, has fewer options, including options about sex. HIV and other sexually transmitted infections (STIs) thrive in exactly those conditions,” AHF said.

Girls Act Targets Health, Education And Leadership

The organisation said its Girls Act programme seeks to prevent HIV and sexually transmitted infections, support girls living with HIV to remain on treatment, reduce unplanned pregnancies and help girls stay in school.

According to AHF, the initiative had more than 4,500 girls actively participating as of 2026.

The programme operates across four areas: health, education and livelihoods, leadership, and results.

Under its health component, girls living with HIV receive support to remain on treatment, while HIV-negative participants learn how to prevent infection and make informed decisions.

The programme also provides free menstrual health products to girls and surrounding communities. It teaches participants to make and maintain reusable sanitary pads to improve access beyond direct supplies.

On education and livelihoods, AHF said the programme supports girls who wish to return to school and provides life-skills training and business support to those who have dropped out.

Its leadership component creates opportunities for mentorship, advocacy and access to resources to enable girls to take active roles in their communities.

“Girls are turning up empowered, able to negotiate safe sex and exercise bodily autonomy.

“Negotiating safe sex is the difference between exposure and protection, and bodily autonomy is not a slogan but a public health asset.”

AHF Seeks Government Funding

AHF called on federal and state governments to incorporate the Girls Act model into HIV, education and youth development plans, with dedicated funding for its activities.

The group said the funding should cover menstrual health products, skills training and start-up support for out-of-school girls, assistance for girls returning to school, leadership opportunities and stronger links to HIV testing, treatment and care.

“This means dedicated budget lines for menstrual health, so no girl misses school for want of a sanitary pad; skills training and start-up support that reach out-of-school girls where they live; support for girls to return to, and stay in, school; leadership platforms for girls in schools and communities; and clear pathways linking young people to HIV testing, treatment and care,” the advocacy group said.

The organisation also urged stakeholders in the national HIV response to give greater attention to the needs of girls and young women.

“Some will say the country has more pressing priorities. They should weigh the cost of inaction: new infections among young people, lifelong treatment, interrupted schooling and lost productivity.

“Prevention that also builds livelihoods and leadership is among the smartest investments a government can make.

“Our girls have shown what is possible when someone invests in them. They have earned the right to be treated as a key population in the national response, not as an afterthought.”

Viral Video Sparks Debate Over Racism and Perfume in China

By Hadiza Abdulkadir 

A viral video showing Chinese passengers covering their noses around an African woman has triggered a heated debate online over racism, cultural differences and the use of perfume.

The woman, identified on X as Teebebe (@Acupoftii_), appeared to interpret the passengers’ reaction as racist. The video has since attracted widespread attention, with social media users offering competing explanations for the behaviour.

One of those responding was X user Zhao DaShuai, who argued that the incident may have had less to do with race and more to do with the strength of the woman’s perfume.

“It’s your perfume,” Zhao wrote.

He said many East Asians carry a variant of the ABCC11 gene linked to reduced production of certain compounds associated with underarm odour. According to Zhao, this may mean people in East Asia are less accustomed to strong fragrances.

The claim has prompted further debate, with some users questioning whether covering one’s nose should be interpreted as evidence of racial discrimination, while others argue that the gesture could have been a simple reaction to an unfamiliar smell.

Scientists have established a relationship between variations in the ABCC11 gene and differences in underarm odour, although the prevalence of the relevant variants varies considerably between populations.

The genetic explanation, however, does not establish why the passengers in the video covered their noses. Nor does the video, by itself, provide enough context to determine whether the behaviour was motivated by racism, discomfort with a strong fragrance, or another reason.

The incident has nevertheless revived an online conversation about race, personal fragrance and cultural differences in perceptions of smell, highlighting how an apparently ordinary gesture can carry very different meanings across cultural and racial contexts.

Suspected Rabid Dog Bites 18 in Kano Community as NFSS Deploys Personnel

By Uzair Adam 

The Nigerian Forest Security Service (NFSS), Kano State Command, has deployed personnel to Garko Local Government Area to track and contain dogs suspected of carrying rabies after one dog reportedly attacked and bit 18 people in the area.

The State Commander, Abdullahi Al’ameen, disclosed this in a statement signed by the command’s Public Relations Officer, Usman Abdullahi-Umar, on Sunday in Kano.

Al’ameen said the command received a distress report at about 2 p.m. that a dog suspected to be rabid had attacked residents in Garko town.

According to him, the dog initially attacked and bit 11 people in Garko town before moving into neighbouring communities, where it attacked seven additional residents.

“The dog had so far bitten 11 persons in Garko town before moving to neighbouring communities, including Raba, Kadage, Gurjiya and Dausai,” he said.

The commander added that the command had received another report indicating that two more dogs were suspected to have contracted rabies in the area.

He said personnel from the NFSS Garko Division, led by the Divisional Forest Officer, Auwalu Muhammad, had been deployed to the affected communities to track and contain the suspected rabid dogs.

Al’ameen urged residents of Garko and neighbouring communities to remain vigilant and promptly report sightings of stray or suspected rabid dogs to the nearest NFSS office or other security agencies.

He also advised anyone bitten by a suspected rabid dog to seek immediate medical attention, stressing the importance of prompt treatment.

Al’ameen assured residents that the NFSS would continue to monitor the situation and take necessary measures to prevent further attacks.

At Least Six Inmates Die in Suspected Cholera Outbreak at Kano Prison

By Hadiza Abdulkadir

At least six inmates have died within a week following a suspected cholera outbreak at the 115-year-old Kurmawa Maximum Prison in Kano, with Amnesty International Nigeria calling on the authorities to declare an emergency and take immediate action to prevent further deaths.

The rights organisation said a number of inmates are currently receiving treatment as the suspected disease continues to spread within the prison. It warned that the actual number of deaths could be higher.

Amnesty particularly raised concern over the condition of critically ill inmates and called for their immediate transfer to hospitals for appropriate medical treatment.

The organisation also expressed concern about the large number of awaiting-trial inmates held at the facility, noting that some prisoners can spend years behind bars without being convicted of a crime.

According to Amnesty, overcrowding, poor sanitation, inadequate food and limited access to healthcare remain serious problems in Nigeria’s correctional facilities.

It warned that failure by the authorities to respond urgently to the situation at Kurmawa Prison could result in additional deaths and potentially amount to arbitrary deprivation of life, a serious human rights violation under international law.

Amnesty called for urgent measures to contain the suspected outbreak and improve conditions in Nigerian prisons, stressing the need for the country to ensure that the treatment of inmates complies with human rights obligations and international standards.

Study Links Short-Form Videos to Reduced Brain Activity in Cognitive Control Regions

By Muhammad Abubakar

Frequent exposure to short-form videos on platforms such as TikTok, Instagram Reels and YouTube Shorts may affect brain systems involved in self-control, attention and memory, according to emerging research.

A neuroimaging study found that watching preferred short videos was associated with increased activity in the amygdala, a brain region involved in emotion and reward, while areas of the prefrontal cortex responsible for cognitive control showed reduced activity. The researchers said the effect was more pronounced among people with lower levels of self-control.

Other recent research has reported similar concerns. A 2026 systematic review and meta-analysis covering 71 studies and nearly 98,300 participants found that greater use of short-form video was associated with poorer cognitive performance, particularly in attention and inhibitory control.

A separate study published in npj Science of Learning also found that learning through fragmented short videos was associated with poorer memory accuracy and reduced activity in several brain regions involved in information integration, cognitive control and semantic processing.

However, researchers caution that the findings do not mean that watching TikTok, Reels or Shorts literally “deactivates the brain.” Most studies examine associations or short-term changes in brain activity, and more longitudinal research is needed to establish whether frequent short-form video consumption causes lasting cognitive changes.

The findings nevertheless add to growing concerns about the cognitive effects of endless scrolling and rapidly changing, algorithmically selected content, particularly when such platforms are used for prolonged periods.

Yobe and the Apollo Outbreak: A Question of Who We Serve

By Ali Tijjani Hassan

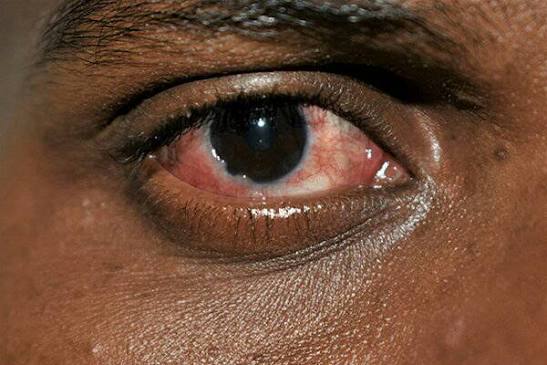
There is a difference between a public health system that performs well on paper and one that performs well in people’s lives, and Yobe State is currently teaching us these differences in real time. For over ten days, reports of viral conjunctivitis (Apollo), as it is popularly called, have been spreading across parts of the state. Yet the silence from official quarters has been almost as consistent as the outbreak itself. No public advisory. No visible coordination. No reassurance that anyone in authority is even watching. And silence, in public health, is never neutral. It either means nothing is happening, or it means something is happening and no one has thought to tell the people living through it. Neither of these answers is acceptable. Considering the communicable nature of this outbreak, it is essentially as contagious as yawning. The system should work, and the response should be in place.

I say this, not out of pessimism, because pessimism is cheap and the outbreak deserves better than cheap reactions. Yobe is not a state without human resource capacity. We have a significant number of epidemiologists and precision medicine experts. We have disease surveillance officers, laboratory scientists, environmental health officers, and public health professionals—a full formation of expertise that many states would envy. So, the question is not whether we have the people. The question is whether the system built around those people is actually working, or has quietly become one optimised for reporting rather than responding. Because here is an uncomfortable truth: a health system can hit every donor indicator, produce every glossy report, receive every award, and still fail the basic test of protecting the community it exists to serve. KPIs are not the same as outcomes. A dashboard is not the same as a warned public. You can be commended internationally and still be invisible locally, and that gap between what is reported upward and what is felt on the ground is where public trust quietly erodes.

What sharpens this concern is that we are not operating in isolation. This outbreak is not affecting only Yobe State; it’s spread across northeastern states. Take Adamawa State as an example: it’s currently responding to a similar outbreak of viral conjunctivitis. They already declared a pandemic and activated warning and response systems since the 7th of August, 2026. Coincidentally, Bauchi State is experiencing a cholera outbreak; the state government has been activating its cholera response system since the 1st of August, 2026. These are not distant or hypothetical benchmarks; they are neighbours, operating under comparable constraints, demonstrating that a coordinated response is possible when the will and the system align. So if they can move, what exactly is holding us back?

Is it a failure of surveillance itself, or a failure to verify what surveillance already picked up? Is it risk assessment sitting somewhere in a queue? Is it plain bureaucratic inertia, the kind where information exists but no one owns the decision to act on it? Or is it something more troubling: a culture where we wait for numbers to become undeniable before we treat them as urgent?

I raise these questions not to indict anyone by name, but because public health, by its very design, is supposed to be anticipatory. Its entire justification is that it acts before catastrophe forces it to. A surveillance system that produces reports without triggering timely action has collected data successfully but has failed in its actual purpose. And there is something quietly troubling about a community that learns of a potential outbreak through word of mouth before it hears a single word from the institutions constitutionally responsible for its well-being. That is not just a communication gap. It is a trust gap, and trust, once eroded in public health, is far harder to rebuild than any epidemic curve.

The remedy is not complicated. If there is no outbreak, say so clearly and to everyone, not just to donors. If there is one, say so. If an investigation is currently in progress, please communicate that clearly. If interventions have begun, say so. None of this requires perfect information. It requires the basic respect of keeping people informed while the work is being done. Because silence is not surveillance, and a response no one can see is barely a response at all. The people of Yobe do not need another award ceremony. They need a system that notices early, speaks plainly, and moves before the numbers force its hand. In the end, the truest measure of a public health system was never going to be what it reports about itself. It is what the people living inside it actually experience.

Ali Tijjani Hassan is a public health professional who writes from his personal quarantine after being infected with the Apollo.